Streamlining ABA Practices: Specialized Modalities, Authorization Tracking, and Supervision in Lumenality
ABA practices keep supervision and authorizations on track by tracking each service type on its own terms. Every ABA CPT code carries its own rendering-provider level, its own authorized units and its own role in supervision. When those three facts live in the session record, RBT supervision stays on schedule and authorizations are less likely to run out unnoticed.
How do ABA service types differ?
ABA service types differ by who delivers them, who is present and whether the treatment plan changes during the session. CMS's State Medicaid and CHIP ABA Toolkit summarizes the CPT codes and their typical provider types:
- 97151: behavior identification assessment by a qualified health care professional (QHP), such as a BCBA.
- 97152: supporting assessment delivered by a technician under the direction of a QHP.
- 97153: adaptive behavior treatment using an established plan, delivered by a technician such as an RBT.
- 97154: group treatment for two or more patients, delivered by a technician.
- 97155: treatment that modifies the plan, delivered by a QHP, which may include directing a technician at the same time.
- 97156 and 97157: guidance for caregivers by a QHP, for one family or for several families together.
- 97158: group treatment with protocol modification, delivered by a QHP.
Each code is billed in 15-minute units. States often differentiate these codes by the credential level of the billing provider, such as BCBA, BCaBA or RBT. The toolkit names 97153 as the most frequently billed ABA code in Medicaid fee-for-service. A single client's week can include three or four of these codes, each with its own authorization line.
Where do teaching modalities fit?
Teaching modalities change how data is collected, not which provider level a code requires. Discrete trial training (DTT) breaks skills into small, structured trials with clear instructions and consistent reinforcement. Naturalistic developmental behavioral interventions (NDBIs), such as Pivotal Response Training and the Early Start Denver Model, embed teaching in play and daily routines. A review in the Journal of Autism and Developmental Disorders describes NDBIs as delivered in natural settings. The same review notes their shared control between child and therapist and their use of natural contingencies.
Both approaches rest on the principles of applied behavior analysis, and one client's program can use both. A structured session might call for trial-by-trial data. A naturalistic session may suit frequency, duration or interval recording. Whatever the modality, the session note should show the targets addressed and the data collected, because that note supports every billed unit.
What are the BACB supervision requirements for RBTs?
RBTs must receive ongoing supervision for at least 5 percent of the hours they spend providing behavior-analytic services each calendar month. The BACB's RBT Handbook sets the structure:
- At least two face-to-face, real-time supervision contacts each month.
- Direct observation of the RBT providing services during at least one of those contacts.
- At least one individual contact, while the other may be a small group of 2 to 10 RBTs.
- Records of service hours, supervision dates and duration, format, observation dates and supervisor names.
BCaBAs work under supervision as well. The BACB states that a BCaBA may provide services only under the supervision of a BCBA, and that BCaBAs may supervise RBTs. States and payers can add their own rules on caseloads, ratios or the number of RBTs one supervisor oversees.
The 5 percent figure is a credentialing minimum, not a clinical target. The CMS toolkit notes that clinical practice guidelines recommend roughly 10 to 20 percent supervision relative to direct treatment hours. Clients with complex needs, newly trained staff and telehealth services may call for more.
Is supervision billable?
Some supervision is billable, and the state Medicaid manual or the payer decides the details. The CMS toolkit's general rule is that a direct, medically necessary service to one client can be billed. Training, employment supervision and administrative work generally cannot. Billable supervision is often tied to 97153, 97155 and 97156, such as live clinical direction during a session or caregiver guidance.
A BCBA's observation can therefore count toward BACB supervision without being a billable unit for that payer. Track supervision time and billable time separately, so meeting one never hides a gap in the other.
How do authorizations and supervision connect?
Authorizations and supervision connect through the codes. Each code on an authorization draws down separately, so 97153 hours can look healthy while 97155 units run low. When 97155 units run out, a BCBA's time with the client may no longer be billable, yet the RBT still needs supervision. Tracking each code's drawdown next to supervision hours shows that gap before it opens.
Underuse and overuse both carry costs. Unused authorized hours can leave a client short of the recommended intensity of services. Hours delivered beyond the authorization produce sessions no one can bill, and they can draw attention in an audit.
Audits show why matching the code, the provider and the note matters. The HHS Office of Inspector General's audits of Medicaid ABA payments recommended that Wisconsin pay 97153 claims based on the rendering provider's level. The audits also recommended documentation showing what changed in the treatment protocol for 97155. For the request side, our guide to mastering prior authorizations covers benefits checks, medical necessity and reauthorization.
How Lumenality connects supervision and authorizations
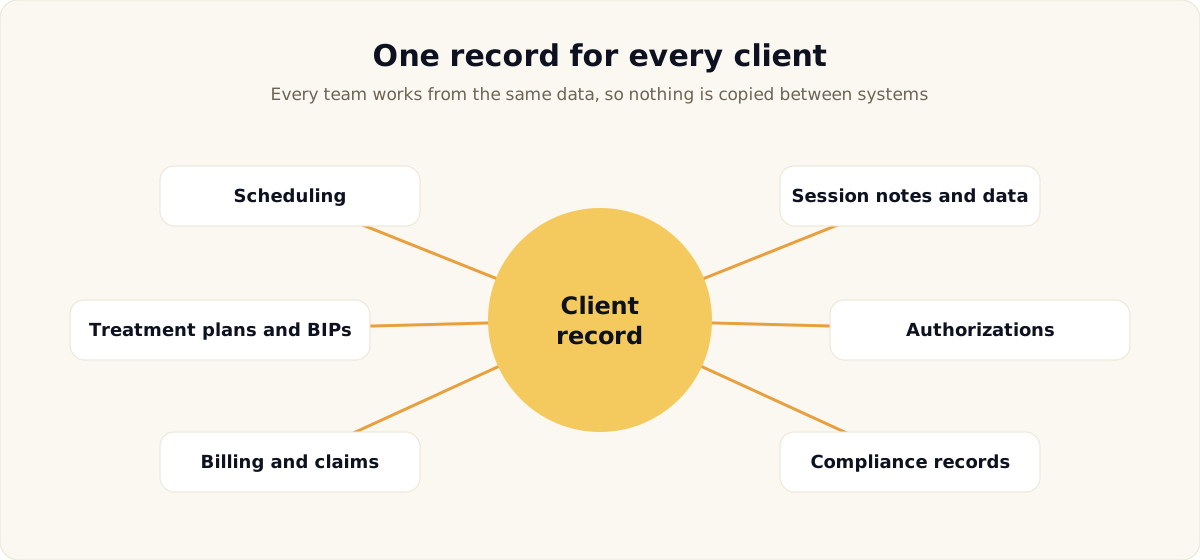
Lumenality keeps supervision, authorizations and clinical data in one client record, so each session updates all three at once.
- Data for every modality. Trial-by-trial, frequency, duration and interval data collection on mobile devices, with IOA recording, a program library and automated graphs.
- Supervision tracking. Supervision hours and ratios are tracked for each RBT, and BCBA co-sign workflows give supervisors a clear review step.
- Authorizations by code. Authorizations draw down by CPT code per session, with a warning at 80 percent of units used and a flag before the end date.
- Credentials in the record. Staff credentials sit next to the services each person delivers. Our credentialing guide for ABA providers covers the payer side.
- Claims from the note. The session note becomes the claim line, with CPT code, units and authorization, and rule-based checks run before it goes out.
- EVV where required. EVV is captured when the note is signed, with an exception queue and a claim gate.
Fieldwork hours, CEU tracking and a video training library keep professional development in the same place. When a claim does come back, our guide to ABA denial management explains how to read the reason codes.
Every practice runs on its own single-tenant deployment, with its own database and encryption keys, and an audit trail records who opened each record. Explore Lumenality for ABA, or request a demo to see supervision and authorization tracking with your own caseload.
*This article was created with AI assistance and reviewed by the Lumenality team.*