Effective Denial Management for ABA Billing: Reducing Roadblocks to Reimbursement
Effective denial management for ABA billing works as a loop. Read the reason codes on each 835 remittance, group denials by cause, and fix each cause where it started. Then correct and resubmit or appeal, and track the claim until paid. Prevention matters most, because common ABA denials trace back to authorizations, documentation, coding, eligibility or filing deadlines.
ABA billing has traits that make denials expensive. Services are billed in 15-minute units across a family of CPT codes, and many payers cap those units through prior authorization. A client may have several sessions a week, so one unnoticed problem can repeat on every claim. A steady loop turns each denial into a fix that protects the next claim.
Why do ABA claims get denied?
ABA claims get denied for a handful of recurring reasons, and each one starts somewhere upstream of the claim. The claim adjustment reason codes maintained by X12 name them precisely. Knowing the usual causes tells you where to look first:
- Authorization. Sessions delivered before approval, more units than authorized, or dates after the authorization ended. Code 197 means the authorization was absent, and code 198 means it was exceeded.
- Documentation. Missing or unsigned session notes, a missing supervisor co-signature, or a note that does not support the units billed. Code 50 means the payer did not consider the service medically necessary.
- Coding. Billing eight units of 97153 when the note supports six, or billing 97155 for a session an RBT delivered. Code 185 means the rendering provider is not eligible to perform the service billed.
- Eligibility. Coverage that ended or changed between sessions. Code 27 covers expenses incurred after coverage terminated.
- Timely filing. A claim that reached the payer after its filing window. Code 29 means the time limit for filing has expired.
Coding problems deserve a closer look in ABA, because each code has a defined provider level. CMS's Medicaid ABA toolkit describes 97153 as treatment delivered by a technician under the direction of a qualified health care professional. It describes 97155 as treatment that modifies the plan, delivered by the professional. States often differentiate these codes by the credential level of the billing provider. Some state programs also require a modifier such as 95 or GT when 97155 is delivered remotely.
What do the codes on an 835 tell you?
The codes on an 835 remittance tell you who owns each adjustment and why the payer paid differently than you billed. X12 describes reason codes as the explanation for why "a claim or service line was paid differently than it was billed." Each reason code travels with a group code, which X12 says generally assigns responsibility for the adjustment amount. There are four:
- CO: Contractual Obligation.
- PR: Patient Responsibility.
- OA: Other Adjustment.
- PI: Payor Initiated Reduction.
A PR line usually becomes part of the family's balance. CO, OA and PI lines need a check against your contract and the claim itself. Sorting by group code first keeps write-offs, patient statements and corrections in separate queues.
Remark codes add the detail. X12 remittance advice remark codes explain an adjustment that a reason code already describes. For example, N54 says the claim information is inconsistent with pre-certified or authorized services. M62 flags a missing, incomplete or invalid treatment authorization code. Reading the reason code and remark code together often points straight at the cause.
Is a rejection the same as a denial?
No: a rejection means the claim never entered the payer's processing system, while a denial is a decision made after processing. CMS's guide to checking Medicare claim status describes two levels of front-end edits. A 999 acknowledgment reports whether the file was readable. A 277CA rejects individual claims that fail basic implementation-guide checks. A rejected claim gets no claim number, so it needs a fix and a new submission rather than an appeal.
The same guide warns against resubmitting while a claim is still in editing, because the second copy creates a duplicate. X12 code 18 marks an exact duplicate claim or service. Watching acknowledgments claim by claim helps you avoid both problems.
How does the denial management loop work?
The denial management loop works in five steps, and each step feeds the next one.
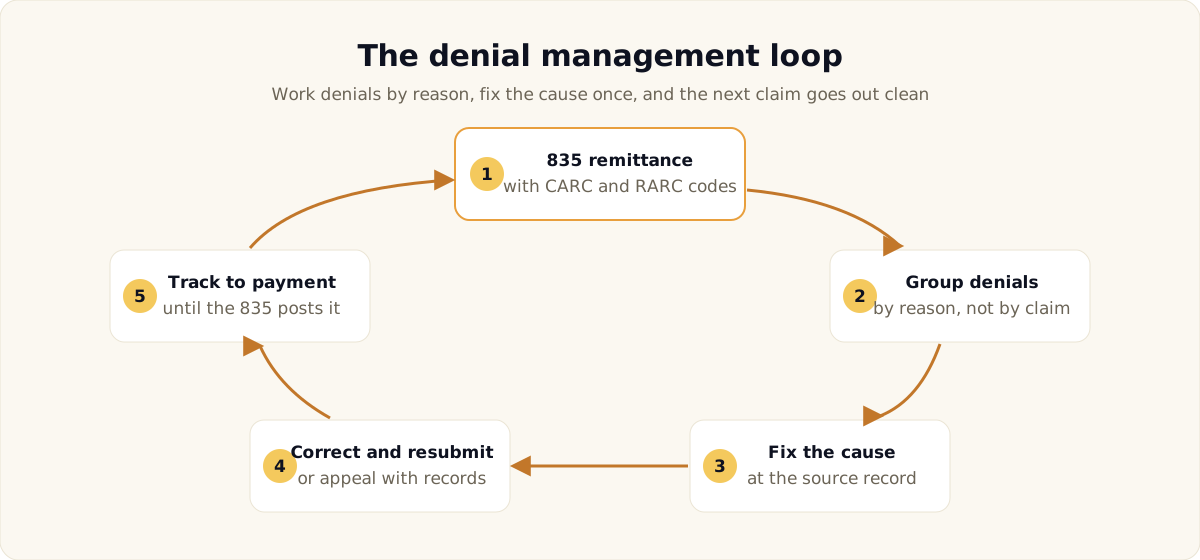
- Read the remittance. Post every 835 line, and capture the group code, reason code and remark codes for each denial.
- Group denials by reason. Count denials by reason code, payer and service code each week, so patterns show up early.
- Fix the cause at the source. Update the authorization, the note template, the payer's modifier rule or the provider's enrollment, not just the one claim.
- Correct and resubmit, or appeal. Send a corrected claim when the claim was wrong, and appeal with clinical documentation when the payer was wrong.
- Track the payment. Keep each denial open, with an owner and a follow-up date, until the payment posts or the balance is resolved.
The third step is the easiest one to skip under pressure. Fixing only the claim leaves the cause in place, and the same denial returns with the next batch. A denial that keeps coming back is a process problem, not a billing problem.
Appeals follow each payer's own levels and deadlines, so keep them on file per payer. A strong appeal points to the session note, the treatment plan and the graphed data behind the billed units.
Where does denial prevention start?
Denial prevention starts at intake and continues through every session note. Each common cause has an upstream fix:
- Authorizations: track units by CPT code and start reauthorization early. Our guide to mastering prior authorizations covers the full cycle.
- Eligibility: check coverage before the first session and again whenever a plan may have changed.
- Credentials: confirm each rendering provider is enrolled with the payer before they bill. Our post on credentialing and revenue cycle management shows how enrollment gaps turn into denials.
- Documentation: make each note show what was done, by whom, for how long and toward which goal.
Documentation carries extra weight in ABA. The HHS Office of Inspector General's audits of Medicaid ABA payments found that, in Wisconsin, all 100 sampled enrollee-months included improper or potentially improper claim lines. Its recommendations covered session note content, documentation of 97155 protocol changes, and paying 97153 based on the rendering provider's level. The CMS toolkit notes that reviews after payment can end in recoupment. A denial you prevent today is far easier than a payment returned later.
How Lumenality supports the loop
Lumenality is an ABA-only EHR and practice-management platform that builds the claim from the same record as the session. The session note and its data become the claim line, so the CPT code, units and authorization come from one place. Rule-based checks run before the claim goes out, and a held claim points to a specific issue. Our walkthrough of how Lumenality checks ABA claims covers those checks in detail.
- Clearinghouse built in. Claims go out as 837P through Stedi, with 999 and 277CA acknowledgments tracked on each claim.
- Remittances that post themselves. 835 remittances post payments automatically, with the remittance details attached to the claim.
- Eligibility and status. Real-time eligibility (270/271) and claim status (276/277) checks run through the same connection.
- Authorization drawdown. Authorizations draw down by CPT code per session, with a warning at 80 percent of units used and a flag before the end date.
- EVV claim gate. For programs that require EVV, the visit is captured when the note is signed, and a claim gate holds claims with unresolved exceptions.
- Denial workflows. Denials land in a worklist where your team assigns, corrects, resubmits or appeals them.
Every practice runs on its own single-tenant deployment, with its own database and encryption keys. Every record access lands in an audit trail. If you'd like to see the loop with your payers, we'd be glad to walk you through it in a demo.
*This article was created with AI assistance and reviewed by the Lumenality team.*