The EHR Choice: Why Single-Tenant Delivers Long-Term Value for Small ABA Practices
A single-tenant EHR delivers long-term value when its price stays predictable and the system grows with you. Over several years, per-seat pricing climbs with every hire. Percentage-of-collections pricing climbs with every paid claim. A flat rate per practice moves with your provider tier, not with each login. Switching costs belong in the math too.
The first-year invoice is a poor guide to what an EHR will cost. A small ABA practice that adds RBTs, payers and a second location will pay a very different bill in year five. Pricing the whole term, including the cost of leaving, is how you compare vendors fairly.
What makes up the total cost of an EHR?
Total cost is the subscription plus everything you pay to make the system work. The monthly fee is rarely the only surprise. The larger costs usually sit around it:
- Subscription: the monthly fee, and the rule that makes it rise.
- Clearinghouse: per-claim or per-transaction fees, sometimes under a separate contract.
- Add-ons: features sold separately, such as a guardian portal, EVV or extra reports.
- Setup and training: one-time fees to configure the system and teach your staff.
- Workarounds: staff hours spent on spreadsheets, double entry and separate portals.
- Switching: the cost of leaving, paid once but best priced from the start.
Workarounds rarely appear on an invoice, but they appear in payroll. Systems built for a broad mix of specialties often miss ABA basics such as authorization unit tracking or supervision ratios. Someone then rebuilds that work by hand. Each hour spent copying data between a data sheet, a billing tool and a clearinghouse portal is a real cost.
How do per-seat, percentage and flat-rate pricing compare over time?
Each model ties your bill to a different number, and that number decides how the bill grows. Compare the models against your growth plan, not against this year's headcount.
Per-seat pricing
Per-seat pricing ties the bill to the number of people with logins. ABA practices grow by adding RBTs, and each RBT needs access to collect data and document sessions. The BACB RBT Handbook requires supervision for at least 5% of each RBT's service hours every calendar month. Supervision can include reviewing progress notes and data sheets, so supervisors need access too. Under per-seat pricing, every hire adds a line to the invoice.
Percentage of collections
Percentage-of-collections pricing ties the bill to revenue. The fee rises when collections rise, even if the vendor's work for you has not changed. A practice that adds a payer, opens a second site or recovers denied claims shares that gain with its software vendor. The model can look cheap in a slow first year and expensive in a strong fifth year.
Flat rate per practice
A flat rate ties the bill to the size tier of the practice. Lumenality charges one flat monthly rate per practice by provider count, with plans starting at $599 a month (Solo). Every tier's rate is listed on our pricing page. Clearinghouse and AI usage are billed at agreed-to rates, and long-term contract pricing is available. There are no per-seat charges, no setup fees and no percentage of collections.
AI usage only applies if your admin chooses to use AI at all. Every AI feature in Lumenality is optional, off by default and controlled by the practice's admin. Our post on optimizing ABA billing in Lumenality explains where optional AI fits and where rule-based checks do the work.
Why does one record lower the long-term cost?
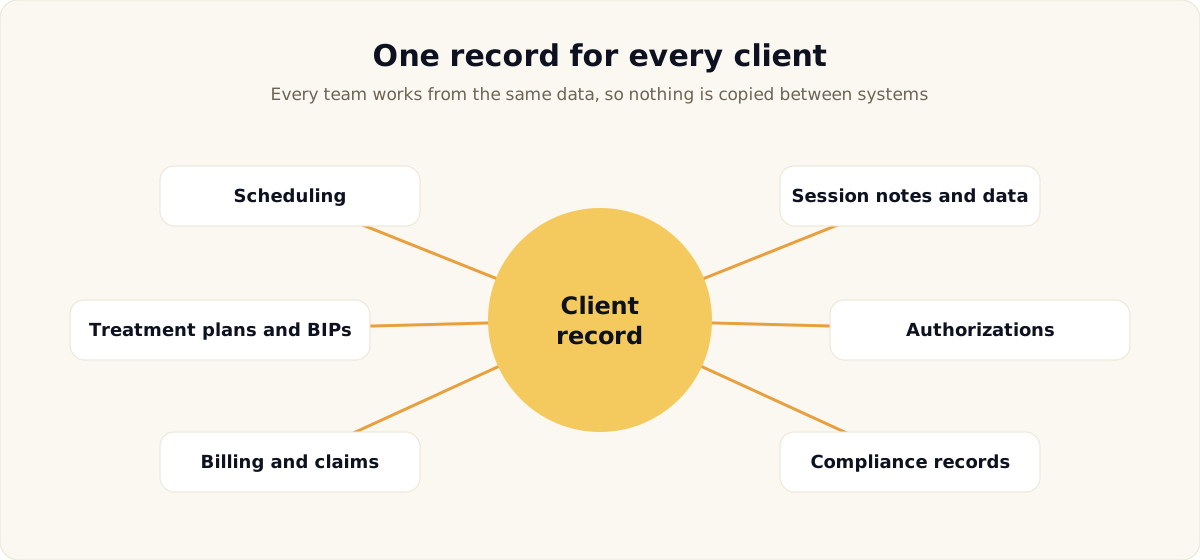
One record lowers cost because every separate system is another contract, another login and another place to re-enter the same session. In Lumenality, one client record shares scheduling, session notes and data, treatment plans, authorizations, billing and claims, supervision hours and credentials. Clinicians document a session, and billing builds the claim from that same data, with no re-entry between systems.
The clearinghouse is part of the same platform. Claims go out through the built-in Stedi integration as 837P transactions, with 999 and 277CA acknowledgments tracked per claim. 835 remittances post payments automatically, and enrollment is handled with the practice. Real-time eligibility (270/271) and claim status (276/277) checks run inside the platform as well.
What does it cost to change or switch EHRs later?
Switching later costs time, staff attention and some data quality, even when the move goes well. Pricing it now keeps a cheap first contract from turning into an expensive fifth year. Plan for these costs:
- Migration: an assessment of what your current system can export, then mapping and checks. Some data may need re-keying.
- Training: days of staff time away from clients while the team learns new screens.
- Payer enrollment: ask whether claim and remittance enrollments must be redone with a new clearinghouse.
- Old records: retention duties continue after the old contract ends, so the archive needs a home.
- Overlap: a period when you may pay for two systems while the new one goes live.
For Lumenality, most practices go live in about 2 to 6 weeks. The steps are the agreement and BAA, a data-migration assessment, 3 to 5 days of staff training and a one-day go-live. Import scope is confirmed after reviewing sample exports from your current system. Exit terms matter just as much, and our post on avoiding vendor lock-in lists what to get in writing.
The cost of change inside the system
Change does not stop once you go live. The AMA's CPT Editorial Panel has accepted revisions to the adaptive behavior codes 97151 to 97158, plus new codes, effective January 2027. Each decision appears in the panel's published summaries of panel actions. Ask each vendor whether code updates, payer rule changes and new reports are part of the subscription or billed as projects.
Program rules shift as well. Medicaid.gov explains that the 21st Century Cures Act requires states to implement EVV for Medicaid personal care and home health services. Where EVV applies to your services, Lumenality captures it when the note is signed. An exception queue and a claim gate keep claims with unresolved EVV exceptions from going out.
Why does a single-tenant design hold its value?
A single-tenant design holds its value because your environment grows with you instead of being replaced. Every Lumenality practice runs on its own dedicated deployment, with its own database and its own encryption keys. Your configuration and data stay separate from every other practice's. Updates to a dedicated deployment can often be more predictable than changes rolled out across a shared platform.
Security is part of the same long-term picture. Each deployment adds AES-256 encryption at rest, TLS 1.2+ in transit, role-based access control, MFA and an audit trail of record access. Lumenality signs a BAA with every customer. Our comparison of single-tenant and multi-tenant EHRs explains the architecture in more depth.
Pricing the next five years
Before you sign, write down your expected headcount, caseload and payer mix for the next few years. Then run each vendor's pricing model against that plan:
- How does the bill change when you add an RBT, a BCBA or a location?
- How does it change when collections grow?
- Which clearinghouse, add-on, setup and training fees apply?
- Are code updates and payer rule changes included?
- What would it cost to leave, and what do the exit terms promise?
The answers turn a sticker price into a total cost of ownership. For the full selection process, see our guide on how to choose an EHR for a small ABA practice.
*This article was created with AI assistance and reviewed by the Lumenality team.*